
Washington would like states to enjoy the freedom to change their hospital laws. To help them exercise that freedom correctly, it has brought a scoring system and a very large pile of money.
The Trump administration's $50 billion Rural Health Transformation Program rewards states for, among other things, loosening or repealing certificate-of-need requirements. KFF Health News reports that six states have included such changes in their plans. Federalism remains a cherished principle, especially when the federal government can award points for it.
Half the five-year fund is divided equally among states; the other half depends on a range of factors, including policy commitments. So this is not an order to repeal a law or lose every dollar. It is a financial incentive to discover that Washington's preference was your local preference all along. The distinction is important, particularly to whoever has to write the application.
Certificate-of-need laws require approval for certain new facilities, expansions or equipment. They can let an established hospital fight a competitor's arrival. KFF describes one approved North Carolina hospital stuck in legal challenges for three years before construction began. A community can apparently demonstrate its need for a hospital and then spend several years demonstrating its need for the demonstration to end.
Make powerful people uncomfortable.
Subscribe to Democrawonk.
There is a real case for changing that arrangement. Criticism of these laws crosses party lines, and Tennessee's recent move to unwind most remaining requirements was bipartisan. An incumbent's ability to obstruct a rival does not become a public service because the obstruction arrives on hospital stationery.
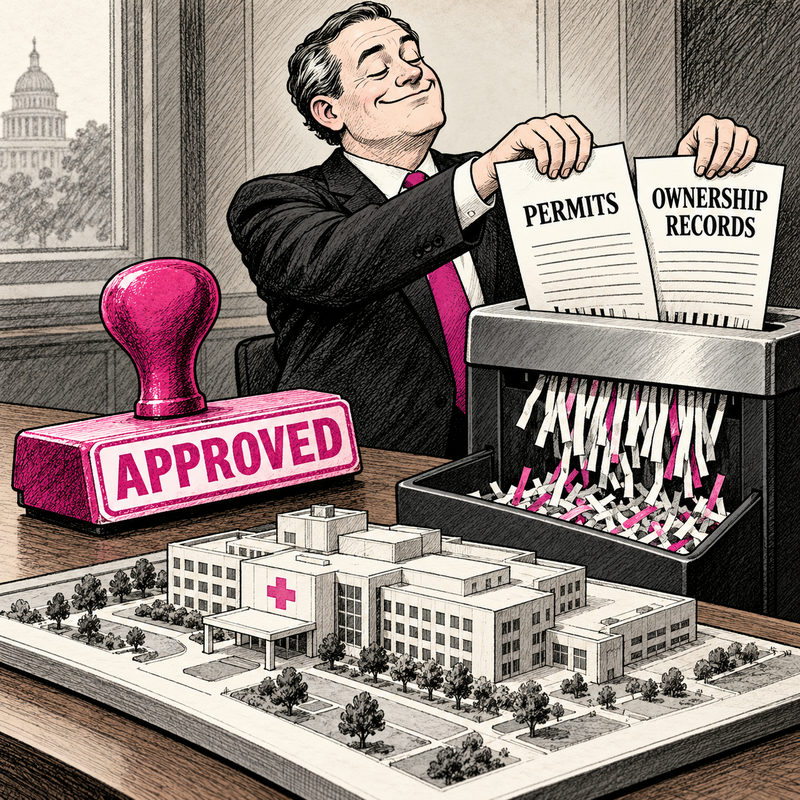
But watch what else may leave with the approval process. A state-health-policy expert told KFF that repeal can eliminate ownership and financial disclosures unless states replace those reporting requirements. Later, when officials need to understand a health system's finances or private-equity arrangements, the records may not be there.
That is quite a two-for-one offer: stop making a hospital prove it should expand, and potentially stop learning enough about the owner to see what is expanding. The first change concerns permission. The second concerns visibility. They fit neatly into the same paperwork pile if nobody looks too closely at the paperwork.
Hospital leaders also warn that new competitors could concentrate on profitable markets while leaving rural providers with harder cases. Those are warnings, not proof that repeal will produce that result. The immediate, documented transaction is simpler: an administration offering rural-health money is giving states an additional reason to remove particular rules.
The applicant will know exactly how important those changes are to its federal score. Whether the state can still follow the hospital's ownership and finances depends on what it keeps after the points have been awarded.
Comments
Have something to say? Give this story a heckle.
Comment Rules
Argue the point. Add a joke. No threats, harassment, hate speech, spam, private personal information or unsupported accusations. First-time comments and comments with links are moderated. Full Comment Rules
Loading comments…
Questions or deletion requests? Contact Us. We retain comments and moderation records until removed. Only hashed email identifiers are stored for comment accounts.